


Coccydynia
Practice Essentials
Coccyx pain (tailbone pain) can frustrate patients and significantly impair quality of life, but relief is possible.
Coccyx pain was first documented in 1588, and the term coccydynia was coined by Simpson in 1859. Currently, the term coccydynia is used somewhat more commonly than coccygodynia. The 2 terms are interchangeable, however, and indicate pain localized to the coccyx. Neither term specifies the underlying etiology. Coccyx pain can occur from local trauma or a tumor, but many cases are idiopathic, with no identifiable cause.
Patients with coccyx pain often report that their physicians minimize, dismiss, or belittle their symptoms. Indeed, many physicians may have a bias against patients with coccyx pain, which has been referred to as the “lowest” form of “low back pain.” Tailbone pain is often relatively severe and persistent, causing significant compromise of the patient's ability to perform or endure various activities. Physicians who understand coccydynia and the available treatment options can provide a great service to this otherwise neglected patient population.
Diagnosis
The patient's response to injection of local anesthetic agents, with or without corticosteroids, can provide helpful information regarding whether the patient's pain generator has been accurately identified. However, the injection response may not be considered truly diagnostic of whether the pain generator is a specific anatomic structure unless the injection is performed with the guidance of fluoroscopy or other imaging aids. Similarly, if large volumes of fluid are injected, extravasation from the targeted site decreases the diagnostic specificity.
Plain radiographs are typically the initial imaging study of choice for patients with coccydynia, especially in cases of focal sacrococcygeal trauma. Plain radiographs may reveal fractures, abnormal sacrococcygeal curvature, osteophytes, or dislocations of the sacrococcygeal junction or intracoccygeal segments.
Lumbosacral magnetic resonance imaging (MRI) would be most helpful in cases in which the coccygeal pain is suspected to be referred from anatomic structures located more superiorly within the spine (ie, at the lumbar or sacral regions).
Computed tomography (CT) scanning and/or MRI of the pelviscan be helpful in cases in which intrapelvic pathology (ovarian, cervical, colon, testicular, or prostate cancer or their associated metastases) is suspected.
Management
Physical therapy for coccydynia may involve manually working on tight, painful muscular structures such as the levator ani, coccygeus, or piriformis muscles. Myofascial release techniques may be used. Local modalities also may be helpful.
Surgical treatment for coccydynia includes coccygectomy, in the form of partial or complete surgical removal of the coccyx.
One possible mechanism for persistent coccydynia is excessive activity or sensitivity of the ganglion impar, thus creating sympathetically maintained coccyx pain. Local injection of an anesthetic can effectively block the ganglion impar and thereby relieve coccyx pain.
When the primary pain generator is thought to be at the sacrococcygeal joint, local injection can be administered to this site.
The authors of this article have found that in cases in which ischial bursitis is suspected as a substantial component of the patient's buttock pain, local injection of the bursa can be performed either with local anesthetic alone (diagnostic injection) or with corticosteroids (therapeutic injection).
Ablation can be used to intentionally destroy nerve fibers at the coccyx, so that those nerves can no longer send pain signals to the brain. Thermocoagulation of the ganglion impar using radiofrequency ablation (RFA) has been reported. Ablation can also be accomplished chemically (eg, by carefully injecting neurotoxic agents such as phenol and/or ethyl alcohol directly onto the targeted nerve tissues). These coccygeal ablation injections have been in clinical use for multiple decades and thus are no longer considered experimental.
Osteopathic, chiropractic, or other "manual medicine" techniques to mobilize the coccyx are sometimes performed by clinicians who feel that the sacrococcygeal segments of a given patient have decreased mobility.
Anatomy
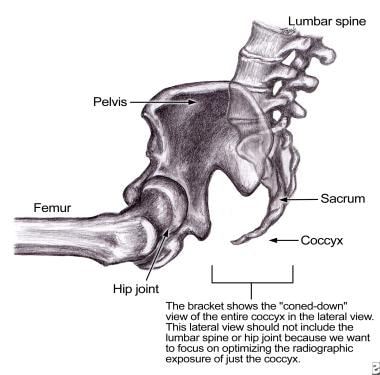
The coccyx is the terminal end of the spine, just inferior to the sacrum. The human coccyx is often considered a vestigial remnant or corollary of a tail; thus, the coccyx is colloquially referred to as the tailbone. The word coccyx comes from the Greek word for cuckoo, the name apparently having been derived from the tailbone’s shape, which resembles that of a cuckoo’s beak.
The human coccyx is composed of 3-5 individual segments (coccygeal vertebrae), with variations occurring with regard to the number of segments, the overall angulation (curve) of the coccyx, and the degree of articulation versus fusion between the individual segments. In 80% of patients, the coccyx is made up of 4 coccygeal vertebrae. Typically, the coccyx is concave anteriorly and convex posteriorly.
The base of the coccyx articulates with the sacral apex via the sacrococcygeal junction. The sacrococcygeal articulation and intracoccygeal articulations contain fibrocartilaginous discs, somewhat comparable to the intervertebral discs present at other spinal levels. The apex (distal tip) of the coccyx is typically rounded, but may be bifid. (See the image below.)
Muscles and ligaments
In humans, the coccyx serves important functions, including as an attachment site for various muscles, tendons, and ligaments. Physicians and patients should remember the importance of these attachments when considering surgical removal of the coccyx.
Muscles inserting on the anterior coccyx include the levator ani, which is sometimes considered as several separate muscle parts, including the coccygeus, iliococcygeus, and pubococcygeus muscles. This important muscle group supports the pelvic floor (preventing inferior sagging of the intrapelvic contents) and plays a role in maintaining fecal continence. A midline component is the anococcygeal raphe, by which the coccyx supports the position of the anus. Muscles originating on the posterior coccyx include the gluteus maximus, which is the largest of the gluteal (buttock) muscles and which functions to extend the thigh during ambulation.
Multiple important ligaments attach to the coccyx. The anterior and posterior sacrococcygeal ligaments attach the sacrum to the coccyx (similar to the functions of the anterior and posterior longitudinal ligaments spanning cervical, thoracic, and lumbosacral spinal segments). Laterally, the transverse process of the coccyx serves as an attachment site for the lateral sacrococcygeal ligaments (arising from the inferolateral sacrum), as well as for fibers from the sacrospinous ligament (arising laterally from the spine of the ischium) and the sacrotuberous ligament (connecting the sacrum with the ischial tuberosity, but with fibers attaching to the coccyx as well).
Function
The coccyx serves somewhat as a weight-bearing structure when a person is seated, thus completing the tripod of weight bearing composed of the coccyx and the bilateral ischium. The ischial weight-bearing surfaces are, more specifically, at the ischial tuberosities and inferior rami of the ischium.
The coccyx bears more weight when the seated person is leaning backward; therefore, many patients with coccydynia sit leaning forward (flexing at the lumbosacral and hip regions), which shifts more of the weight to the bilateral ischium rather than the coccyx (see the images below). Alternatively, patients with coccydynia may sit leaning toward one side so that the body weight is exerted mainly on one ischial tuberosity or the other, with less pressure on the coccyx. Such side leaning may lead to concomitant ischial bursitis in addition to the antecedent coccydynia.
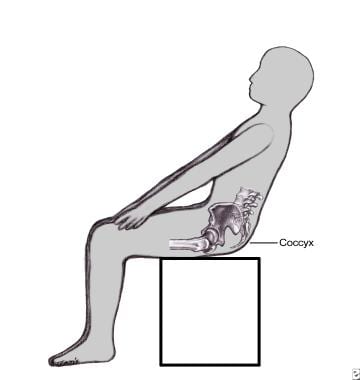 cyx pain (coccydynia, or tailbone pain) is typically worse when the patient is sitting. Often, the pain is even worse when sitting leaning slightly backward, since this increases the weight bearing on the coccyx, as shown in this image. Dynamic radiographs of the coccyx involve obtaining coned-down (focused) views of the coccyx while the patient is seated (eg, in his or her most painful position). Often, this involves having the patient lean backward 0-40°, depending on the symptoms. Radiographs obtained in this position are compared with those obtained in a non–weight-bearing position (eg, side lying) to assess for instability or dislocations in the seated position.
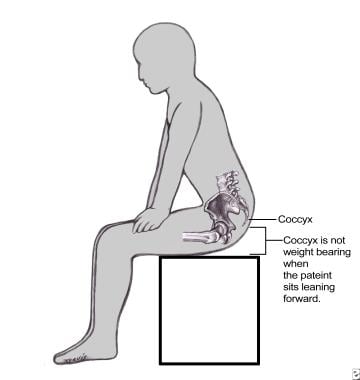 Patients with a painful coccyx often find it more comfortable to sit leaning slightly forward, as shown in this image. This forward-leaning position minimizes any weight bearing on the coccyx itself and thus minimizes the exacerbation of coccyx pain. As shown, when a patient sits leaning forward, most of the weight bearing occurs bilaterally through the inferior ischial regions of the pelvis and the posterior thigh (femur) regions.
Etiology
Causes of coccyx pain include trauma, fractures, dislocations, and primary or metastatic malignancies. (A retrospective study by Dang et al of primary spinal tumors indicated that those of the sacrum or coccyx are more likely to be malignant. Sources of acute, abrupt trauma include internal trauma (eg, giving birth) and external trauma (eg, falling onto the coccyx). Nonabrupt trauma may include prolonged sitting. Tailbone pain may begin after certain medical procedures, such as colonoscopy. Some cases of coccydynia are idiopathic, without any identified etiology.
One risk factor for coccyx pain is aging; degenerative changes of the sacrococcygeal junction and the intracoccygeal junctions, as well as fusion at these sites, seem to increase with age.
A gender-specific risk factor in females is trauma related to giving birth; substantial pressure may be placed on the coccyx as the baby descends through the mother's pelvis.
Epidemiology
Coccydynia is considered to be relatively uncommon, but data are lacking on the exact incidence and prevalence of the condition.
Coccydynia is seen in males and females; however, women seem to be affected more frequently than men. As previously mentioned, one gender-specific risk factor in females is trauma related to giving birth; the coccyx may endure substantial pressure as the baby descends through the mother's pelvis.
Coccydynia can occur in children and adults. Degenerative changes of the sacrococcygeal junction and the intracoccygeal junctions, as well as fusion at these sites, seem to increase with age.
Prognosis
While some patients with coccydynia have complete relief via natural recovery over time, others develop a persistent, chronic pain syndrome at the coccyx region.
One proposed reason why coccyx pain seems to be more chronic than other injury sites is the inability to immobilize or brace the site (eg, as compared with bracing and casting that is available for injuries at the wrist, ankle, or others, but is not available for similar immobilization at the coccyx). This may contribute to delayed or prolonged recovery as well as the development of chronic, persistent, intractable pain syndromes.
Once the coccyx pain has become chronic (persisting for more than 3-6 mo), it may be less likely to resolve by natural recovery alone, more likely to continue indefinitely, more likely to be resistant to treatment, and more likely to require a multimodal treatment approach (eg, oral medications combined with local injections).
Early interventions (eg, oral medications, injections, physical therapy) are presumed to decrease the chance that acute coccydynia will develop into chronic coccydynia. This may be considered a reason for aggressive nonsurgical treatment early on, to potentially decrease the chances of lifelong pain and disability.
Although coccydynia is generally not associated with increased mortality, it is often associated with substantial morbidity. Patients with coccydynia often report severe and persistent pain that compromises functional activities requiring sitting and diminishes their quality of life.
One case series indicated that a positive coccygeal discogram is correlated with better outcome from surgery, but these results were based on small numbers, including just 2 surgical patients who had positive preoperative discograms and 2 surgical patients who had negative preoperative discograms. Further, the usefulness of a positive discogram at predicting surgical outcome intuitively seems to be contraindicated by a separate, histologic study showing that disc degeneration at the sacrococcygeal joint in 5 patients was associated with poor surgical outcome in all 5 cases.
History
The history obtained from a patient with coccydynia involves details regarding the coccydynia itself and other underlying conditions that may refer pain to the coccyx region. Questions relate to the following:
-
Localization of pain - The patient should be asked to indicate or point to the painful site or sites
-
Severity of coccyx pain - The patient should be asked to rate the level of coccygeal pain (0-10 scale) when it is at its best and at its worst and to indicate overall pain severity
-
Duration and onset date of coccydynia - The patient should be asked whether any identifiable traumatic incident, recent or remote, occurred
-
Exacerbating factors - The patient should be asked whether there is pain associated with, for example, prolonged sitting or sitting on hard versus soft surfaces, as well as with sexual intercourse, standing up after sitting, or bowel movements
-
Sitting tolerance - The patient should be asked to quantify how many minutes of sitting can be tolerated before the pain mandates changing position
Other elements of the patient's history that should be obtained include the following:
-
Cushions tried - Such as donut cushions, which have a circular hole in the middle, or wedge cushions, which have a triangular wedge cut out posteriorly
-
Oral medications tried and response to these
-
Interventional pain management procedures and response to these - Such as caudal or other epidurals, local anesthetic blocks, and steroid injections, as well as whether these were administered blindly or guided fluoroscopically
-
Gastrointestinal (GI) symptoms – Constipation, diarrhea, bright red blood per rectum, melena (black, tarry stool), and fecal incontinence (GI workup, such as GI consult, colonoscopy, or rectal exam)
-
Urinary symptoms - For instance, urinary incontinence or dysuria (urinary diagnostic workup, such as urology consult or urinalysis)
-
Female intrapelvic history - Such as uterine fibroids or ovarian cysts
-
Female obstetric history - Childbirth, vaginal or cesarean delivery, and any associated difficulties at the time
-
Female menopausal status - Premenopausal, perimenopausal, or postmenopausal
-
Lower limb neurologic symptoms - Such as radicular pain or lower limb numbness or weakness
-
Concomitant ischial bursitis - Such as unilateral or bilateral ischial buttock pain due to leaning to either side to avoid sitting with pressure on the midline/coccyx region
-
Body weight - Such as any significant increase or decrease in body weight preceding the onset of the symptoms
-
History of cancer - Especially colon, prostate, ovarian, cervical, testicular, or other intrapelvic malignancies.
-
Risk factors for cancer - Blood per rectum, abnormal vaginal bleeding, unexplained weight loss, fevers, or chills
Physical Examination
Palpation
Sacrococcygeal palpation involves identifying and exerting pressure onto the sacrococcygeal junction and the coccyx and noting whether the presenting symptoms localize well to that site (ie, exquisite tenderness at the coccyx and/or sacrococcygeal junction, with only mild or absent tenderness at adjacent structures).
Some clinicians palpate the coccyx via an internal/external approach; using a gloved hand, they place 1 or 2 fingers inside the rectum (anterior to the coccyx) and, with another 1 or 2 fingers, palpate externally (posterior to the coccyx). In this way, some clinicians also attempt to assess for increased or decreased sacrococcygeal mobility. Patients with severe coccydynia may have difficulty tolerating this examination.
Palpation of other (noncoccygeal) lumbosacral structures is an important aid in ruling out pain generators from the ischial bursae, sacroiliac joints, lumbosacral facet joints, and lumbosacral or gluteal muscles.
In one study, 25 out of 30 (83%) patients with a bone spicule at the distal coccyx had a "pit" noted in the overlying skin.
Additional assessments
Other aspects of the physical examination include the following:
-
Skin inspection – Direct visual inspection of the skin over the coccygeal region is important. An underlying pilonidal cyst may produce visible discharge, local rash, or a visible skin opening (fistula). In addition, inspecting for a local dimple/divot may be relevant, because in one study, as noted above, 25 (83%) of 30 patients with a bone spicule at the distal coccyx had a "pit" noted in the overlying skin.
-
Neurologic examination - Strength, sensation, and muscle-stretch reflexes can be assessed throughout the bilateral lower limbs to evaluate for any lumbosacral radiculopathy
-
Lumbosacral range of motion - This can be assessed in multiple planes, including documentation of pain with these motions, particularly if the presenting symptoms are reproduced
-
GI and gynecologic physical examination - Depending on the patient's history and the clinician's expertise, abdominal and gynecologic physical examinations may be performed; manual digital rectal examination can assess for hemorrhoids or other intrarectal masses
-
Diagnostic Considerations
Conditions to consider in the differential diagnosis of coccyx pain include the following:
-
Coccygeal fracture
-
Sacrococcygeal dislocation
-
Intracoccygeal dislocation (dislocation of one coccygeal segment from another)
-
Intrapelvic malignancy and/or metastatic lesions
-
Ischial bursitis
-
Sacroiliac joint pain
-
Ovarian cyst
-
Fibroid uterus
-
Pilonidal cyst
-
Sacral insufficiency fracture
-